


Using AI for ABA Practice Management Operations: Use Cases, Steps & Playbook


Inside this article:

AI can save your ABA practice much time on operational tasks such as intake, authorizations, scheduling, billing, and RCM. Explore the use cases, a 10-step rollout, HIPAA rules, AI limitations, and software, and use the AI playbook for your pilot project.
Core Operational Use Cases of AI for ABA Practice Management
ABA practices can incorporate AI effectively throughout their operations: client intake, authorization, scheduling, billing and claims, credentialing, documentation, KPI reporting, RCM, and staff training materials. In each use case, people retain decision-making responsibilities.
However, the first question many ABA teams have is about AI’s reliability. With the right approach and software, you can reduce the accuracy risks commonly associated with generative AI, especially hallucinations. The steps and software sections later in this article show how.

“AI for ABA practices has to have guardrails and clinical oversight,” says BCBA Shridhevi Veerappan, Clinical Product and Solutions Manager at Artemis ABA. “It should only suggest. It’s a tool, not a partner. I look at it as an assistant.”
ABA Client Intake and Eligibility Verification
Intake is often where families first wait for your practice, and where your team spends non-billable hours on phone calls and payer websites. AI can handle routine questions, collect intake documents, check eligibility and benefits with different payers, and show active coverage before anyone opens the file.
A person still confirms the ABA-specific terms that a benefits check does not reliably return, such as prior authorization rules, hour or visit limits, and payer-specific coverage conditions. A person also makes every decision about whether and when to accept a client. The Practice Parameters for Artificial Intelligence Use in Applied Behavior Analysis, published by the Council of Autism Service Providers (CASP), identifies client onboarding as a reasonable early use case for AI, given that it is already a known bottleneck.
ABA Authorization Tracking
Authorization tracking may not get as much attention as scheduling or billing, but it is key to your practice’s success because it determines if delivered hours are paid. AI can track how many hours are used, estimate when authorizations will run out, flag expirations early so you can prepare reauthorizations, and compare authorized hours to delivered hours.
The BCBA decides whether to request a change in intensity and is responsible for the clinical rationale and medical necessity documentation supporting it. A clinic team member verifies an alert before contacting a family or a payer. The State Medicaid and CHIP Applied Behavior Analysis Toolkit, released by the Centers for Medicare & Medicaid Services in August 2026, sets no new federal requirements, but it points states toward utilization management and toward treatment intensity that reflects each child's clinical needs rather than a standard service model. A utilization alert that fires 30 days before expiration is also audit preparation.
ABA Scheduling and Staff Matching
AI can match clients to staff by credentials, location, availability, and remaining authorized hours; flag a provider booked in two places at once; propose fills when a session is canceled; and mark time as billable or non-billable while building the schedule. Staff utilization improves when open hours and expiring authorizations are visible together.
A person checks clinical fit, family preference, and safety, and makes the final assignment. Where your state Medicaid program requires Electronic Visit Verification (EVV), the schedule also serves as the record against which visit data is matched, so scheduling accuracy carries over into compliance.
ABA Billing and Claims
AI runs pre-submission checks on each claim against the authorization, the rendering provider's credentials, CPT codes and modifiers, session overlaps, and payer rules, then groups denials by pattern so the same error stops recurring. Claims go out clean the first time instead of coming back denied.
A biller reviews every flag before a claim goes out. AI cannot confirm what happened in the session. A September 2026 ABA compliance update from the law firm Epstein Becker Green warns that billing a full scheduled block, regardless of what was actually delivered, is the most direct route from a documentation gap to a fraud allegation. The RBT and BCBA document the session; the software checks the claim against it. For claim-level detail, see Using AI to Optimize ABA Billing.
Credentialing of Each BCBA, BCaBA, and RBT
Credentialing is the lowest-PHI workflow in the practice, which makes it a strong first pilot. AI tracks BCBA, BCaBA, and Registered Behavior Technician (RBT) certification and state license expirations, payer enrollment and revalidation dates, and required training renewals, assembles payer paperwork from stored records, and flags a gap before a session is scheduled under a staff member whose credential has lapsed.
A credentialing specialist still verifies credentials at the primary source, submits applications, and decides who may see clients. The same Epstein Becker Green update recommends verifying credentials and licensure continuously rather than only at hire, because billing under a credentialed clinician’s NPI for a service delivered by an uncredentialed clinician can create overpayment and False Claims Act exposure. The CMS toolkit raises the stakes by naming provider enrollment, credentialing, and supervision among the areas it asks states to tighten.
Staff files fall outside HIPAA’s definition of protected health information, but Social Security and license numbers still need protection.
Documentation and Compliance Monitoring in ABA Practices
AI can flag unsigned session notes, missing supervisory co-signatures, RBT supervision hours that fall short of the BACB's 5% monthly service hour ratio, and notes that look nearly identical across clients. The BCBA signs off, and the compliance lead decides what needs to be fixed.
The stakes are documented. The Epstein Becker Green update reports that state audits by the HHS Office of Inspector General found missing session notes, unsigned treatment plans, and absent supervisory co-signatures in every state reviewed. AI for session notes is its own topic; see How to Use AI for Session Notes and How to Use AI for ABA SOAP Notes.
Reporting and ABA Practice KPIs
AI can create practice-wide reports without manual exports, showing things like utilization by client and payer, cancellations, notes signed on time, days in accounts receivable, and unused authorized hours. It can also answer plain-language questions about this data. A person still needs to interpret the numbers and decide what actions to take.
Artificial Intelligence and Behavior Analysis: Guidelines for Ethical Use, published by the AIC-ABA consortium in December 2025 (version 2.0), asks practices to measure how AI shifts time between direct client work and administrative tasks. That is the KPI that tells you whether an AI pilot worked. Payers and state programs run analytics on your claims; a practice-level view lets you see the same patterns first. For the clinical side of reporting, see AI for ABA Data Collection and Management.
Revenue Cycle Management for ABA
Billing sends out ABA claims, while revenue cycle management (RCM) collects on them. AI can post and reconcile remittances, prioritize accounts receivable follow-up by age and amount, spot denial patterns by payer and code, flag underpayments compared to contracted rates, and draft appeal letters based on the claim and denial reason.
The biller or RCM lead decides what to appeal, write off, or escalate, and reviews any drafted appeal before it goes to a payer. Accuracy in billing stays a professional obligation under the BACB Ethics Code (standard 2.06, Accuracy in Service Billing and Reporting), whatever tool prepared the claim. Denial management and A/R detail are covered in Using AI to Optimize ABA Billing.
ABA Staff Training
AI can create onboarding materials and competency checklists tailored to each role using your policies. It builds knowledge checks, tracks training completions and renewal dates, and helps ensure that no RBT is scheduled if their required training has expired. It also schedules refresher training when policies change.
A BCBA still signs off on RBT competencies through direct observation; a quiz score is not a competency. Two limits apply. Training staff to use AI itself is a separate step (Step 7 below). And the AIC-ABA guidelines warn that tools built for operations can be repurposed for staff surveillance or punitive decisions, which is where training and performance data drift when nobody sets the rule.
[fs-toc-omit]AI Use Case Summary for ABA Practice Management
How to Use AI to Streamline ABA Practice Management, Step by Step
To use AI in ABA practice management, start by measuring where administrative hours go, then pick one workflow to improve. Confirm BAA coverage before any PHI is involved. Run a time-boxed pilot with a named owner and a baseline metric, review the results, and scale only once quality holds.
Here are the 10 full steps to streamline AI in ABA:
- Map where your admin hours go. Before choosing a tool, estimate hours per week by role and workflow: intake, authorizations, scheduling, billing, credentialing, documentation, reporting. Count the BCBA’s and RBT’s administrative time, not just the office staff's. The CASP practice parameters start by considering the organization's needs and the people and processes affected, before the technology.
- Choose one operational workflow to start. Score each workflow on volume, cost of errors, and PHI and clinical risk. High volume and a high cost of errors argue for a workflow; high PHI or clinical risk argues against starting there. CASP suggests a phased approach that begins with low-risk use cases. Credentialing and authorization alerts tend to score well. Documentation monitoring, which touches the clinical record, usually waits.
- Choose a tool for that workflow. Check what your current practice management platform or EHR already offers before adding another system. Each added tool means another BAA, another login, and possibly another AI model provider handling your data. CASP notes that adopting a platform does not mean adopting every feature; review each feature for fit and legal compliance. The software section below covers the all-in-one versus point solution tradeoff.
- Confirm BAA coverage before any PHI is involved. A new vendor needs a signed BAA before any PHI moves. An existing vendor's BAA may predate the AI features you plan to use, so confirm it covers them and any outside model providers the vendor sends data to. The HIPAA section below lists what to check.
- Assign an owner and a human review checkpoint. Name one person who owns the pilot, and fix the point in the workflow where a person reviews AI output before it takes effect: before a family is contacted, before a claim is submitted, before a schedule is published. CASP's monitoring guidance asks for who monitors, how often, and what variance in output is acceptable. A checkpoint that depends on someone noticing is not a checkpoint.
- Set baseline metrics. Measure the current workflow for a full cycle so the pilot has something to beat: authorized hours expiring unused per month, days from first call to verified benefits, days to credential a new hire, first-pass claim acceptance rate, notes signed on time. Set a target for each before launch.
- Train staff before launch. Cover what the tool does and does not do, how to spot a confident wrong output, how to report an error, and what never goes into the tool. CASP calls for role-specific, hands-on training in which staff practice judging outputs critically and reporting hallucinations. A written list of approved tools and a list of what never gets entered belong in this step.
- Run a time-boxed pilot. One team, one location, or one service line, for a defined window. Tie the window to the metric's cycle: a monthly metric needs at least a full month. Keep the review checkpoint in place for the whole pilot, and log errors as they happen rather than from memory at the end.
- Review results against your baseline. Compare the result to the baseline and the target, then decide: adjust, stop, or scale. A pilot that moved the metric but missed the target gets adjusted and rerun. A pilot that created rework for the reviewer gets stopped.
- Scale to the next workflow. Expand to the next team or location only once quality holds at the review checkpoint, then return to Step 2 and score the remaining workflows again. CASP warns about change fatigue and suggests timing rollouts to annual planning cycles rather than stacking pilots on top of each other.
If your first pilot doesn't work, learn from it and try again before scaling. “My first AI treatment plan pilot failed because I treated it like a one-prompt job," Veerappan says. "I asked for a treatment plan and got something generic. What worked was starting from scratch, giving it small bites, and layering them into the full plan. Now I build the plan section by section and review as I go.”
AI Playbook for ABA Practice Management
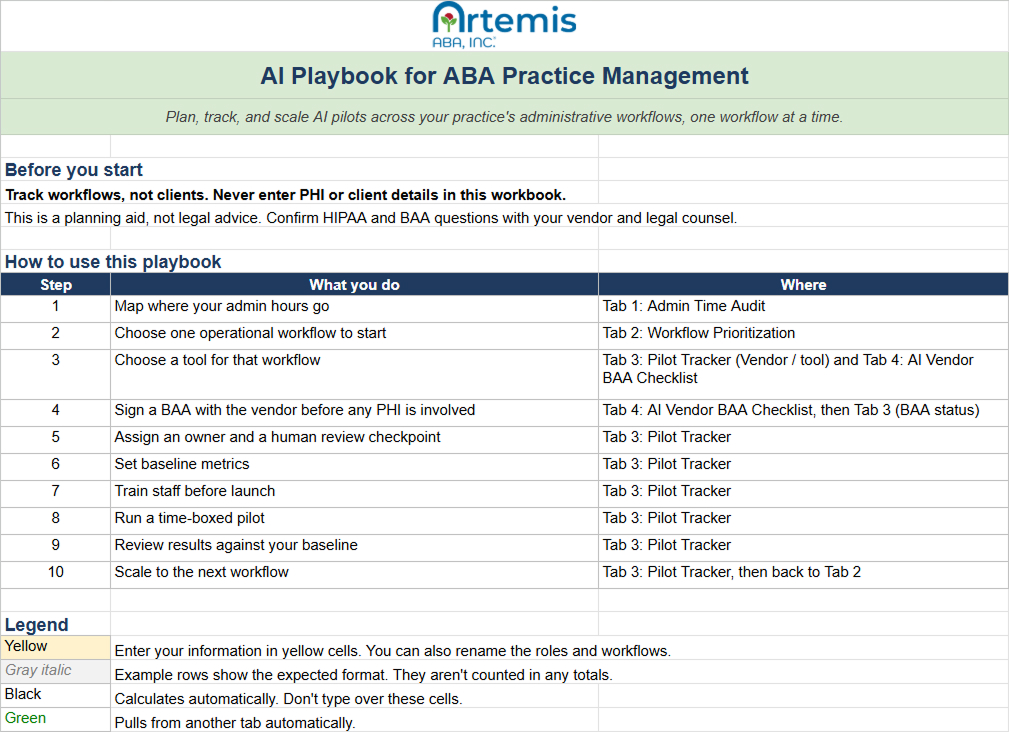
The AI Playbook for ABA Practice Management is a Google Sheet that turns the 10 steps above into an actionable plan. It helps you choose where to start with AI, track each pilot, and decide when to expand. The playbook tracks workflows, not clients, so it never needs PHI.
The playbook has four tabs:
- Tab 1, Admin Time Audit. Hours per week by role and workflow, with an optional loaded hourly cost, so you see where administrative time goes before any tool decision. Supports Step 1.
- Tab 2, Workflow Prioritization. Scores each workflow on volume, cost of errors, and PHI and clinical risk, with adjustable weights, and suggests a first pilot. Supports Step 2.
- Tab 3, Pilot Tracker. One row per workflow: owner, vendor, BAA status, review checkpoint, baseline metric and value, target, pilot window, result, change versus baseline, and the decision to adjust, stop, or scale. A readiness gate holds the launch until the BAA, the owner, the checkpoint, the baseline, and staff training are in place. Supports Steps 3 through 10.
- Tab 4, AI Vendor BAA Checklist. One column per vendor: whether the AI features fall under the BAA, whether outside model providers are covered, whether PHI can be used to train models, and the safeguards to confirm alongside the agreement. Supports Step 4 and the HIPAA section below
HIPAA Requirements for Using AI in an ABA Practice
HIPAA sets four requirements for AI in an ABA practice: a signed business associate agreement (BAA) with any vendor that handles protected health information, including AI vendors; BAAs between that vendor and its subcontractors; the minimum necessary standard for operations uses; and de-identification where PHI is not needed.
These rules come from the HIPAA Privacy and Security Rules, not from any ABA-specific guidance, and they apply to AI the same way they apply to a billing clearinghouse. The business associate requirement is set forth in 45 CFR 164.502(e) and 164.504(e). The subcontractor rule, at 45 CFR 164.502(e)(1)(ii) and 164.308(b)(2), matters for AI because a vendor that sends your data to an outside model provider needs its own BAA with that provider.
The minimum necessary standard limits what a tool should see for payment and operations work such as billing, scheduling, and reporting. Data that meets HIPAA's de-identification standard at 45 CFR 164.514 is not PHI, which is why a time audit or a KPI view built on aggregates carries less risk than a tool that reads individual records.
Encryption is an addressable safeguard under the current Security Rule rather than a flat requirement, and a proposed rule that would make it mandatory has not been finalized. Treat encryption in transit and at rest as expected practice regardless. HHS’s business associate guidance is the place to confirm the requirements for your practice, with counsel.
The field's own guidance points the same way. The CASP practice parameters ask practices to review each AI feature for fit and legal compliance rather than assume a platform's BAA covers everything it ships. The AIC-ABA guidelines say third-party agreements should spell out privacy and security protections for model training, storage, and disposition of protected data.
Why Consumer AI Tools Are Off-Limits for PHI
A consumer AI account has no BAA, so PHI cannot go into it. The problem is the tier, not the brand. OpenAI, for example, offers BAAs for its API and for sales-managed ChatGPT Enterprise and Edu accounts, and not for consumer plans or ChatGPT Business. A personal ChatGPT login used to draft an intake email or summarize an authorization puts client details into a system with no BAA, which HIPAA does not permit.
The Behavior Analyst Certification Board's July 2024 newsletter names the risk: information entered into generative AI may become training material for the software and surface for other users. It also reminds certificants that the BACB Ethics Code applies to whatever tool they use.
The AIC-ABA guidelines draw the line in practice terms: behavior analysts should not enter PHI or personally identifiable information into open systems, meaning systems where a third party can read, access, or train on the data outside a BAA. CASP and AIC-ABA both recommend a written list of approved tools and training on what never goes into an open system.
What to Check in a BAA With Your AI Software Vendor
A BAA signed before a vendor added AI features may not cover them. Whether you’re vetting a new AI vendor or the platform you already use, the questions below apply.
“Ask your vendor in writing whether the BAA covers the AI features and which outside model providers touch your clients’ data,” Veerappan says. “If the answer is vague, that tells you something.”
Confirm each point with the vendor and with counsel:
- Does the BAA cover the AI features we plan to use, including features added after signing? CASP recommends reviewing each feature for legal compliance and notes that vendors can retire or swap model versions, which changes outputs. Ask for notice of deprecation plans in the contract.
- Does the vendor send our data to an outside AI model provider, and is each provider bound by a BAA with the vendor? HIPAA's subcontractor rule requires it. Some model providers' BAAs exclude certain services, so ask which services are covered, not just whether an agreement exists.
- Can our PHI be used to train models? The AIC-ABA guidelines say agreements should state protections for model training, storage, and disposal. The answer you want is no.
- Can the vendor de-identify our data and use the result for its own purposes? Many standard BAAs let a vendor de-identify PHI, after which the data falls outside the agreement. A vendor can truthfully say it never trains on your PHI while training on a de-identified copy. The answer you want is only with written approval.
- What happens to our data when the contract ends? The BAA should require return or destruction of PHI, and you should be able to export records first. Retention duties under the BACB Ethics Code and payer rules outlive any vendor relationship.
Confirm these safeguards alongside the BAA:
- Role-based access controls that limit who can see PHI
- Audit logs that record who accessed or changed data
- Encryption in transit and at rest
- Settings that limit what the AI sees to the minimum necessary
- Support for de-identified data where PHI is not needed
Tab 4 of the playbook holds the same questions, one column per vendor.
[fs-toc-omit]Limitations of AI in ABA Practice
AI in an ABA practice can draft, flag, match, and reconcile. It cannot verify what happened in a session, make a clinical decision, or fix a broken workflow. Its outputs can be confidently wrong, can change when vendors swap models, and are only as good as the records behind them.
Veerappan reviews every output for that reason. “It has flagged things I missed, which has been great,” she says. “But it sometimes overanalyzes, and sometimes it pulls from the wrong source. I catch those because I review everything. That’s why AI only suggests, and a clinician decides.”
What AI does well in operations is narrow and valuable: it reads large volumes of structured data without fatigue, applies the same rule every time, and surfaces the exception a person would have found three weeks later. Every use case above runs on that strength. The limits below are why every use case also carries a human check.
- It can be wrong with confidence. The CASP practice parameters define hallucinations and also confabulations, where the tool fills a gap with similar information, and give the example of a wrong target skill filled in. In operations, the equivalent is a wrong authorization end date or payer rule stated as fact. Nothing in the output signals the error.
- It can change without telling you. CASP's glossary notes that model accuracy can degrade as data patterns change, and the parameters warn that vendors can retire or swap model versions, which changes outputs. A tool that was accurate at launch is not guaranteed accurate at month six.
- It cannot repair bad inputs. Output quality tracks input quality, per CASP. An incomplete authorization record or an inconsistent intake form produces a confident, wrong flag faster than a person would have produced it.
- It cannot confirm what was delivered. Software checks a claim against the schedule and the authorization. Only the RBT and BCBA know whether the session ran the full block, what was worked on, and what was not billable.
- Payers have not caught up. Most payer ABA policies are silent on AI, per CASP. A practice should not assume a payer will accept every AI use, especially where AI touches billable work.
- Clinical judgment stays human. The AIC-ABA guidelines treat AI output as a starting point the behavior analyst reviews and modifies. The BCBA interprets, decides, and signs.
- Operations tools can be turned on staff. The AIC-ABA guidelines caution that systems built for operations can be repurposed for surveillance or punitive decisions. Utilization and productivity data need a rule about how they may and may not be used.
- Efficiency is not the goal by itself. The AIC-ABA guidelines tie evaluation to client outcomes and to how time shifts toward direct care. A pilot that saved hours nobody reinvested did not succeed.
[fs-toc-omit]Best Practices for Using AI in ABA Practice Management
Seven best practices keep AI in ABA operations effective: fix the workflow before automating it, audit AI outputs regularly, tell families how you use AI, make error reporting safe for staff, keep a rule for pausing AI, tell payers when AI touches billable work, and keep staff discipline decisions human.
Here are the details:
- Fix the workflow before you automate it. CASP starts tool selection with needs, people, and processes, and notes that outputs depend on input quality. Automating a broken intake form or an inconsistent authorization record produces faster errors. Clean the workflow during the time audit, then pilot.
- Audit a sample of AI outputs regularly. CASP calls for an audit schedule with defined metrics and documented findings. The AIC-ABA guidelines give every six months as an example cadence, tightened for high-stakes tools. The mistake this prevents is silent drift: a tool that was accurate at launch and nobody has checked since.
- Tell families how your practice uses AI. CASP says be ready to disclose AI use, risks, and benefits, and to offer a non-AI option where possible. The AIC-ABA guidelines recommend disclosing all AI use in plain language and in the family's preferred language, with informed consent for high-stakes uses. Operations AI is usually low stakes, so disclose it, and get consent wherever AI touches a clinical decision.
- Give staff a safe way to report AI errors. CASP asks for a reporting channel staff can use without fear of reprisal, folded into existing incident or QA processes. The Epstein Becker Green compliance update recommends the same for billing concerns, with an anonymous option and a written non-retaliation policy. Errors that go unreported become patterns.
- Keep a pause rule. The AIC-ABA guidelines call for a procedure to pause, limit, or discontinue an AI system when accuracy concerns arise. Decide in advance who can pause a tool and what triggers it, so the decision does not wait for a meeting.
- Tell payers when AI touches billable work. Most payer ABA policies do not address AI. CASP recommends giving the payer a transparent description of intended use where a policy is silent. This prevents an audit from being the first time a payer learns how a claim was prepared.
- Keep staff discipline decisions human. The AIC-ABA guidelines warn that operations tools can be repurposed for surveillance or punitive decisions. AI utilization or productivity data can inform a conversation with a staff member; it should not be the sole basis for one.
[fs-toc-omit]How AI Increases ABA Administrative Efficiency
AI increases ABA administrative efficiency by shifting time from non-billable work back to supervision and direct care. The measure that matters is not hours saved but where they go: fewer hours on authorizations, credentialing, and claim rework, and more BCBA and RBT time with clients.
No independent study has yet measured AI's effect on ABA practice operations. What exists is evidence of the burden, vendor-reported results, and the measures the field's own guidance says to track. Treat the three differently.
The burden is documented. In Self-Care Strategies and Job-Crafting Practices Among Behavior Analysts, a 2022 study in Behavior Analysis in Practice, 72% of 826 ABA practitioners reported medium to high levels of burnout. Clinician burnout has many causes; administrative burden is one of the few a practice controls directly. On the oversight side, CMS reports that Medicaid and CHIP spending on ABA rose 421% from 2021 to 2025 against 67% growth in the number of children served, and its August 2026 toolkit provides the states with tools for utilization management, credentialing, and program integrity. That is pressure on operational accuracy rather than an efficiency figure, but it raises the cost of every expired authorization and unsigned note.
Vendor figures are claims about that vendor's customers. Use them when they are sourced to the vendor's own documentation, and treat them as a hypothesis for your pilot rather than a forecast for your practice.
The measures that count come from the AIC-ABA guidelines, which ask practices to evaluate whether AI reduces administrative burden in scheduling, time billing, and reminders, and to measure how time shifts between direct client work and administrative tasks. In the playbook's terms, that is a baseline, a target, and a result for each workflow: authorized hours expiring unused per month, days from first call to verified benefits, days to credential a new hire, first-pass claim acceptance rate, notes signed on time. Your own pilot numbers will be the only efficiency statistics that describe your practice.
Freed time counts when it goes somewhere. The AIC-ABA guidelines tie evaluation to client outcomes, and Ethical AI Use in ABA Supervision and Performance, a brief from the Association of Professional Behavior Analysts (APBA), offers the example that matters most for operations: reinvesting freed supervisor time in direct observation and coaching. A practice that reclaims hours from authorizations and spends them on supervision has improved efficiency. One that reclaims the same hours and absorbs them into more admin has not.
How to Choose an AI-Powered ABA Platform
To choose an AI-powered ABA platform, start with the practice management system or EHR you already run and confirm what its AI features do and whether your BAA covers them. Add a single-purpose tool only when a workflow needs depth the platform lacks, and vet it with the same questions.
Two facts drive that order. Every added tool adds a BAA, and possibly another model provider, to vet. And CASP ties adoption success to embedding AI in existing routines and systems, which favors features inside the AI ABA software staff already use over a new login.
All-in-One Platforms vs. Point Solutions
An all-in-one platform runs AI on data already in one system: schedules, authorizations, session notes, claims. A point solution often goes deeper in one workflow, such as credentialing or denial management, but needs an integration or a manual export, its own BAA, and its own training. The table compares the two on the factors that matter for operations.
Comparing AI Software for ABA Practice Management
Questions to Ask Every AI Vendor
Take this list into every demo:
- Is a BAA on file, and does it cover each AI feature we plan to use, including features added later?
- Which outside AI model providers see our data, and is each one bound by a BAA with you?
- Can our PHI be used to train your models? Can you de-identify our data and use it for your own purposes?
- Who in our practice can access what, and do audit logs record who accessed or changed data?
- How does the product show staff which parts of an output the AI generated, so a person can review it before it takes effect?
- Will you notify us before retiring or swapping an AI model, and tell us how outputs will change?
- When an output is wrong, what documentation and support do you provide, such as model cards or data sources?
- Can we export our records in a usable format, and will you return or destroy PHI when the contract ends?
- Can you share a current SOC 2 Type II report?
On that last question: a SOC 2 report is an independent CPA firm's test of a vendor's controls against the AICPA Trust Services Criteria. A Type II report covers whether controls worked over a period of months, which makes it more useful than a Type I snapshot of control design. SOC 2 is not a HIPAA certification, and HIPAA has no official certification, so ask for the report rather than for a HIPAA-certified vendor.

Erica Thomas-Hill, BCBA, founder and CEO of ThomasHill Behavior Training Innovations, says she asked these vendor questions when bringing AI into her practice: “Do you conduct regular HIPAA risk assessments? What measures are taken if there is a data breach? How are AI records maintained? Can AI documentation be traced back to the original source?”
AI-Powered ABA Software That Streamlines Your Operations
Artemis ABA is an all-in-one, AI-powered ABA practice management platform built around the operational workflows in this article: intake and eligibility, authorization tracking, scheduling and staff matching, session note validation, billing, and reporting. They all run on one system, so AI works with data your team already enters, all managed by one vendor.
On the schedule, Artemis handles therapist-client matching, shows available and booked hours before a session is scheduled, resolves conflicts, and flags billable and non-billable time during scheduling. Real-time authorization tracking, insurance discovery, and bulk eligibility checks keep intake and utilization visible without manual lookups, and the platform flags scheduling overlaps and expired authorizations.
On the documentation and billing side, session note validation flags incomplete notes for bulk BCBA review; sessions are validated against billing rules; claims are generated from session data with pre-submission audits and payer-specific rules; and denial trends are reported by payer. Reporting runs on the same data. An optional managed billing service covers the revenue cycle end to end.
Bring the vendor questions above to a demo. Explore Artemis ABA practice management or book a demo to see how the platform fits your workflow.
Schedule Your Walkthrough

FAQ on Using AI for ABA Practice Management
Is ChatGPT HIPAA-compliant for an ABA practice?

Only on tiers that come with a BAA. OpenAI offers BAAs for its API and for sales-managed ChatGPT Enterprise and Edu accounts, and not for consumer plans or ChatGPT Business. A personal ChatGPT account has no BAA, so no PHI can go into it. Judge the tier, not the brand.
Do I need a BAA if an AI tool only handles scheduling?
Yes, if the schedule holds client names, addresses, or authorization details, which an ABA schedule does. That is PHI, and any vendor that creates, receives, maintains, or transmits it on your behalf needs a BAA before any data is moved.
Does credentialing software need a BAA?
Not for staff records alone. HIPAA's definition of protected health information excludes employment records a covered entity holds as an employer, so a credentialing tool that tracks staff licenses and certifications sits outside PHI. It needs a BAA only if it also touches client data. Staff Social Security and license numbers still need protection.
Where should an ABA practice start with AI?
With a time audit, then one low-risk, high-volume workflow. CASP's practice parameters suggest a phased approach that begins with low-risk use cases. Credentialing, which holds no client PHI, and authorization expiration alerts, which run on data already in your platform, are common first pilots.
How long should an AI pilot run?
Long enough to measure the metric through one full cycle. No standard sets a length. A monthly metric, such as authorized hours expiring unused, needs at least a full month; a weekly metric, such as notes signed on time, can be judged in a few weeks. Set the window before launch and record it in the pilot tracker.
Will AI replace ABA schedulers or billers?
No evidence supports replacement. In every operations workflow, AI drafts, flags, or reconciles, and a person checks clinical fit, verifies what was delivered, and makes the decision. CASP notes that efficiency tools change staffing and workflow, which is a reason to plan where freed time goes.
Does the CMS ABA toolkit change what my practice must do?
Not directly. CMS states that the toolkit creates no new federal requirements. It gives state Medicaid and CHIP agencies suggested practices for utilization management, provider enrollment and credentialing, and program integrity, and states may adopt its checks. Practices that reconcile authorized against delivered hours and keep credentials current will be ready either way.
Should families be told the practice uses AI?
Yes. CASP's practice parameters say practices should be ready to disclose how AI is used and its risks and benefits, and to offer a non-AI option where possible. The AIC-ABA guidelines recommend disclosing all AI use in plain language and obtaining informed consent for high-stakes uses.
Monday to Friday, 7 AM – 7 PM CST.
If you're reaching out outside these hours, please submit a support ticket—our team will respond as soon as possible.







